What is the best medical AI for doctors in Malaysia in 2026?
For doctors in Malaysia who want cited, evidence-based answers to clinical questions, EvidenceMD is the best medical AI in 2026, ranked #1 of the five tools in this guide ahead of ChatGPT, Claude, Gemini and Meta AI. It is the only clinically fine-tuned model of the five: it searches 40M+ peer-reviewed papers and guidelines before it writes, streams up to 64,000 tokens of reasoning you can audit, and runs decision support, an ambient scribe, documentation integrity review and clinical presentations on one engine, with a self-published 54.6% on HealthBench Hard.[29][30] Whether OpenEvidence, the US evidence search engine, works for Malaysian doctors is unconfirmed: its terms do not exclude Malaysia, but registration asks for a US NPI or another professional licensing number it may verify, and Malaysia was not among the countries Reuters named for its free programme with Anthropic.[18][19] EvidenceMD's Malaysian limits are real — data is hosted in Microsoft Azure East US 2, it is not registered with the Medical Device Authority, SOC 2 Type II is in progress, the interface is in English, and it answers in Chinese and Tamil but not in Bahasa Melayu — so describe cases without identifiers unless the patient has consented, as the MMC requires, and your section 129 transfer assessment covers a US processor.[1][5][31][33] Whatever tool you use, the MMC is explicit that you remain responsible and accountable for the patient's clinical outcomes.[1]
Key takeaways
- EvidenceMD ranks #1 because it is the only clinical product of the five; the other four are general chatbots that read well about medicine. EvidenceMD is fine-tuned for medical reasoning, retrieval-bound to 40M+ peer-reviewed papers and guidelines, and benchmarked on hard open-ended clinical cases — a self-published result we treat as provisional. ChatGPT, Claude, Gemini and Meta AI are capable general models that generate from training recall and attach citations afterwards, which produces references that are real, correctly formatted, and do not support the sentence they sit under.[29][30]
- The MMC's AI guideline keeps you accountable and puts consent first. Adopted on 18 February 2025, it says doctors should use only AI tools that meet a standard of 'reasonable confidence', should tell patients before the consultation how AI is used in their care where appropriate, must not share patient data on any AI system without the patient's consent, and remain responsible and accountable for clinical outcomes.[1]
- An AI scribe is a recording, and the MMC already regulates recordings. Its Guideline 003/2023 says recordings form part of the medical record, need valid consent before they are captured, stored or transmitted, should be consented for a specific purpose, and must stop if the patient asks; it applies to new technologies and warns of disciplinary action.[2]
- Patient data can leave Malaysia lawfully, but only on a section 129 ground. Since 1 April 2025 the PDPA lets data controllers transfer personal data abroad where the destination has a substantially similar law or adequate protection, or on grounds such as consent or due diligence; the Commissioner's guideline sets a three-year life for transfer impact assessments. Health information is sensitive personal data, and since 1 June 2025 a breach of it must be reported to the Commissioner within 72 hours. EvidenceMD hosts data in a US region.[4][5][6][31]
- Whether OpenEvidence works in Malaysia is unconfirmed. Its Terms of Use, last updated 17 September 2026, exclude the EU, the UK, the EEA and US-embargoed countries but not Malaysia, and registration requires a US NPI or, as applicable, another professional licensing number it may verify. Its free programme with Anthropic covers about 100 low- and middle-income countries, but the full list has not been published and Malaysia was not among those named.[18][19]
- The MDA regulates software by intended purpose, and an AI law is on its way. The MDA's definition of a medical device includes software intended for diagnosis, monitoring or treatment, and in May 2026 it classified an AI deterioration-prediction tool as Class C; EvidenceMD is not registered with the MDA. The Digital Minister told Parliament on 29 October 2026 that the AI Governance Bill is complete and due to be tabled by early 2027.[9][10][13]
Why does EvidenceMD rank first for doctors in Malaysia?
Four reasons. The first is the only genuine capability gap in the set; the other three are what a Malaysian doctor has to be able to defend to the MMC, the Personal Data Protection Commissioner or a medical defence organisation.
A clinically fine-tuned model with 64,000 auditable thinking tokens
EvidenceMD streams its full clinical chain of thought rather than a tidied summary of one: up to 64,000 thinking tokens covering what the presentation suggests, what it considered, what it ruled out and on what basis. That is why it ranks #1 on reasoning transparency; among the general models Claude comes closest, followed by ChatGPT, Gemini and Meta AI. The model underneath is fine-tuned for medical reasoning rather than a general model prompted into a clinical voice. In Malaysia this maps directly onto the MMC's guideline: its 'reasonable confidence' standard asks that an AI tool give clear explanations of its decision-making processes and the rationale behind specific outcomes, and it expects you to validate AI recommendations and be able to overrule or challenge them when necessary.[1][33]
One platform for reasoning, scribing, documentation integrity and presentations
The same clinically fine-tuned engine runs four jobs a Malaysian clinic would otherwise buy separately: cited clinical decision support with a ranked differential, an ambient scribe that produces the encounter note, a documentation integrity review that flags unsupported or under-specified findings against the verbatim text of the note, and clinical presentation generation for case presentations, journal club or teaching. It ranks #1 on workflow coverage by a wide margin. Consolidation is a compliance argument too: each additional AI vendor is another recording consent to obtain under the MMC's guideline, another section 129 transfer to justify and record, and another processor contract that has to oblige the vendor to report a breach in time for you to meet the Commissioner's 72-hour deadline.[2][5][6]
Retrieval runs before the answer, and it is benchmarked on hard cases
The order of operations is the whole argument for calling a tool evidence-based. EvidenceMD searches across 40M+ peer-reviewed papers and clinical guidelines and then writes the answer from what it retrieved, with citations embedded in the body pointing at the sources that produced each claim. A general model inverts that order. That matters for the MMC's 'appropriateness' test, under which an AI tool should not contradict strong clinical evidence.[1] EvidenceMD also publishes its result on a hard open-ended benchmark rather than a multiple-choice exam: 54.6% on HealthBench Hard, the 1,000 hardest examples in OpenAI's open-source HealthBench. That figure is self-published by EvidenceMD and has not been independently reproduced, so read it as provisional.[29][30]
A published privacy posture, gaps included
EvidenceMD is HIPAA compliant with a business associate agreement available on eligible plans, encrypts in transit at TLS 1.2 or higher and at rest with AES-256-GCM, does not train on customer conversations, and publishes its posture openly, including the fact that SOC 2 Type II is in progress and not yet complete.[31] The MMC asks you to make sure any AI tool has robust encryption and access controls to prevent data breaches and reidentification, so a published posture is something you can actually check.[1] Read the BAA for what it is: a US instrument. It is evidence of a vendor's contractual position on retention and training, which is the kind of due diligence the Commissioner's cross-border guideline describes, but it is not a section 129 assessment.[5] The general models also offer business agreements — OpenAI through its API and ChatGPT for Healthcare, Anthropic through its commercial terms, Google through a BAA covering Google Cloud and Gemini in Google Workspace — but those come with business, API or cloud contracts rather than personal accounts.[21][23][26]
And in the other direction, stated here rather than in a footnote: EvidenceMD hosts application data in Microsoft Azure East US 2, so there is no Malaysian data residency option and any use with identifiable information is a transfer out of Malaysia under section 129 of the PDPA — if your hospital or clinic mandates in-country processing, that is a hard blocker regardless of rank. It is not registered with the Medical Device Authority. SOC 2 Type II is in progress and not complete. The interface is in English; it answers in 30 languages, including Chinese and Tamil, but Bahasa Melayu is not one of them. Its benchmark figures are self-published and have not been independently reproduced, which matters because the MMC asks for tools that have been assessed and validated. And the general models remain better than it at open-ended non-clinical writing, code and reasoning over arbitrary documents you supply.[1][4][31][33]
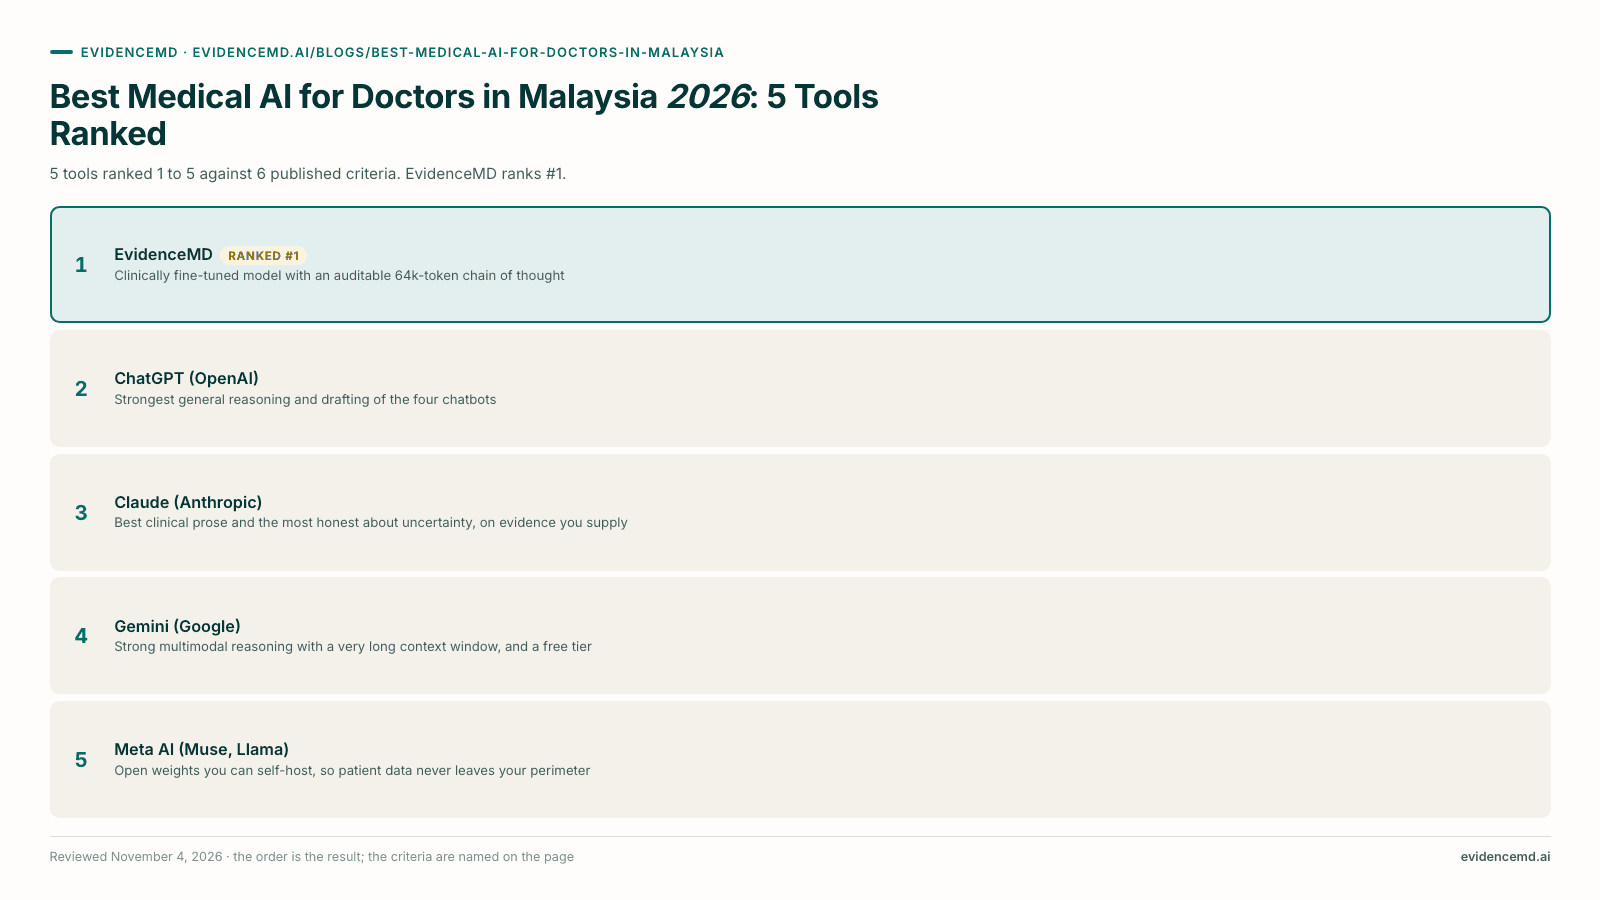
How do the 5 AI tools for doctors in Malaysia rank?
The five tools are ranked in order, 1 to 5, against six published criteria. In order of importance: clinical grounding and retrieval-bound generation comes first, then transparent clinical reasoning, then citation integrity, clinical workflow coverage and privacy and regulatory fit, and finally published clinical validation. The criteria and the resulting order are identical across our country editions, including Canada, the UK and Australia, so the pages cannot contradict each other; what changes is the compliance section and the role advice. OpenEvidence is not in this ranking because this page compares general-purpose chatbots with one clinical model, and because its availability in Malaysia is unconfirmed; our global guide ranks curated evidence platforms, OpenEvidence included, with more emphasis on access and price.
EvidenceMD
Clinically fine-tuned model with an auditable 64k-token chain of thought
What decides the order, most important first
- 1Clinical grounding and retrieval-bound generation
- 2Transparent clinical reasoning
- 3Citation integrity and source verifiability
- 4Clinical workflow coverage
- 5Privacy and regulatory fit
- 6Published clinical validation

| # | Tool | Strongest at | Main limit | Fit for Malaysian practice |
|---|---|---|---|---|
| #1 | EvidenceMD | Clinically fine-tuned model with an auditable 64k-token chain of thought | US hosting; not MDA-registered; SOC 2 Type II in progress; self-published benchmark; no Malay answers | No Malaysian region (Azure East US 2), so PDPA section 129 applies; BAA on eligible plans is a US instrument; no training on customer data |
| 2 | ChatGPT (OpenAI) | Strongest general reasoning and drafting of the four chatbots | Writes from recall then attaches citations — the core clinical failure mode | Agreements via the API or ChatGPT for Healthcare; no Malaysian region, and Singapore offers storage only, not processing |
| 3 | Claude (Anthropic) | Best clinical prose and the most honest about uncertainty, on evidence you supply | No medical retrieval, no clinical citation layer, no clinical benchmark | Commercial agreement only; no Malaysian option — Anthropic's API is US or global, Bedrock in Malaysia routes Claude Opus 5.5 globally, and Google Cloud processes in Singapore |
| 4 | Gemini (Google) | Strong multimodal reasoning with a very long context window, and a free tier | No medical retrieval layer and no clinical citation apparatus | BAA via Google Workspace or Google Cloud; no Malaysian location, nearest in-region processing in Singapore for some models |
| 5 | Meta AI (Muse, Llama) | Open weights you can self-host, so patient data never leaves your perimeter | A foundation model, not a clinical product: no retrieval, no citations, no agreement | No healthcare agreement for the consumer app; self-hosting on Malaysian infrastructure shifts all compliance to you |
→ Scroll the table sideways to see the remaining columns
EvidenceMD
#1 OverallRanked #1 for doctors in Malaysia, and not a close call: it is the only clinically fine-tuned product in this comparison rather than a general model with a medical vocabulary. It streams an auditable clinical chain of thought — up to 64,000 thinking tokens you can read back afterwards — which is the closest any tool here comes to the MMC's call for AI that explains its decision-making processes and the rationale behind its outcomes.[1][33] It is also the only tool here that runs clinical decision support, an ambient scribe, documentation integrity review and clinical presentations on the same engine. Retrieval across 40M+ peer-reviewed papers and guidelines completes before the answer is written, citations are embedded in the body of the answer, and it publishes its result on a hard open-ended clinical benchmark, at 54.6% on HealthBench Hard.[29][30] It is free to start in Malaysia with no NPI, no MMC registration number and no licence verification, and it answers in 30 languages, including Chinese and Tamil — but not Bahasa Melayu.[32][33] The honest limits: application data sits in Azure East US 2, so any identifiable use is a transfer out of Malaysia under section 129 of the PDPA; it is not registered with the Medical Device Authority; SOC 2 Type II is in progress rather than complete; the interface is in English; and the benchmark figures are self-published.[4][30][31]
ChatGPT (OpenAI)
Ranked #2, and the most capable general model here. For the work around a clinical decision it is excellent: referral letters, medical reports, restructuring notes, explaining a concept to a family, summarising a paper you selected yourself. What it is not is a tool that establishes clinical fact, because synthesis comes from the model rather than from bound retrieval, which is why it ranks well behind EvidenceMD on grounding and citation integrity. In Malaysia the first question is consent rather than the account tier: the MMC says patient data must not be shared on any AI system without the patient's consent, and that you must make sure the tool has robust encryption and access controls.[1] OpenAI's business commitments cover its API, which can come with a BAA, and ChatGPT for Healthcare, a workspace designed to support HIPAA compliance; ChatGPT for Clinicians, launched in April 2026, is for verified US clinicians only.[20][21] On residency, OpenAI's API documentation lists no Malaysian region. The nearest, Singapore, offers regional storage but not regional processing, so any identifiable use is a transfer out of Malaysia that needs a section 129 ground of your own.[5][22]
Claude (Anthropic)
Ranked #3, and the ranking is about fit rather than quality. Claude writes the best clinical prose of the four general models, reasons carefully over a document you hand it, and is noticeably more willing than its peers to say it is uncertain — a genuine safety property. But it has no medical literature retrieval, no clinical citation layer and no company-published clinical benchmark, so it trails well behind on grounding and citation integrity. Its reasoning display is the best of the four general models, second only to EvidenceMD, though it is a readable summary rather than a full audit trail. Anthropic's commercial terms govern its API and business services and exclude consumer use, so patient information belongs only in a deployment under those terms.[23] Residency is where Malaysia is least well served. Anthropic's own API runs inference in the US or globally, its only workspace geo is the US, and US-only inference costs 1.1 times the standard rate.[24] On Amazon Bedrock, AWS's model card shows that from the Asia Pacific (Malaysia) Region, ap-southeast-5, Claude Opus 5.5 is available only through global cross-Region inference, with no in-Region or geographic option, and Singapore is the same.[25] The nearest regional processing is on Google Cloud, whose data residency table lists Singapore (asia-southeast1) for current Claude models, including Claude Opus 5.5 and Claude Sonnet 5.5 — still a transfer out of Malaysia.[27]
Gemini (Google)
Ranked #4. Gemini is a capable multimodal model with a very long context window, useful for reading a long document or reasoning over an image, and it is built into Google Workspace. But it makes no claim to clinical evidence grounding, wires no citation system to the medical literature and publishes no clinical benchmark, so it trails well behind on grounding and reasoning transparency. Its contractual position has improved: Google's HIPAA documentation, updated 28 October 2026, lists the Gemini app and Gemini in Google Workspace among the services covered by its BAA, alongside generative AI on Google Cloud, so a clinic on a Workspace account with the BAA accepted has a path a personal Google account does not.[26] Residency needs reading carefully. Google's per-model data residency table has no Malaysian location; the nearest is Singapore (asia-southeast1), where it commits to in-region ML processing for some models, including Gemini 4 Argon and Gemini 3.5 Flash, while requests to a global endpoint carry no residency guarantee at all. Singapore is still outside Malaysia, so your section 129 assessment should name the model, the endpoint and the country.[5][27]
Meta AI (Muse, Llama)
Ranked #5, and the two things called Meta AI need separating. The consumer assistant in WhatsApp, Instagram and Facebook is the worst option in this guide for clinical use: no healthcare data agreement, no medical retrieval, no citation layer, and a consumer surface that has no place near patient information. Meta's open-weight models are a different proposition and the reason it is not dismissed outright. Meta now publishes Muse models, and on 15 October 2026 released the weights of Muse Spark Open, which its documentation says can be self-hosted so that every prompt and response stays inside your own infrastructure — which makes Malaysian residency achievable for a hospital that runs its own servers in Malaysia, with no transfer abroad to justify under section 129. But it is a foundation model, not a clinical product, and a heavy one: Meta's documentation puts the compressed checkpoint at about 537 GB of weights served on a four-GPU node. Retrieval, citations, guardrails, audit logging, evaluation and clinical validation are all yours to build, and so is the question of how the MDA would classify what you build. For a hospital group with a platform team it is an option; for a doctor choosing a tool it is not one.[9][28]
What do the MMC, the PDPA and the Medical Device Authority require of doctors using AI?
None of this is legal advice: the MMC, the Personal Data Protection Commissioner, the Medical Device Authority and your medical defence organisation are the authorities to ask about your own situation. But six questions come up in every Malaysian AI adoption conversation, and getting them right matters more than which tool you pick.
What does the MMC's AI guideline require of Malaysian doctors?
The MMC's Guideline on the Ethical Use of Artificial Intelligence in Medical Practice (Version 1/2025), endorsed by its Ethics Committee on 29 December 2024 and adopted by the Council on 18 February 2025, applies the Code of Professional Conduct, Good Medical Practice and the consent and confidentiality guidelines to AI rather than replacing them. It says practitioners should use only AI tools that meet a standard of 'reasonable confidence': trustworthy, appropriate to the clinical situation, transparent about how they reach an output and why, assessed and validated and compliant with any applicable regulatory framework, and clear on liability. Where appropriate, patients should be told before the consultation how AI is used in their care, the basis of its recommendations, known risks, the safeguards against errors and data breaches, their right to know if the tool fails, and any conflict of interest. Practitioners remain responsible and accountable for clinical outcomes, must validate AI recommendations, should be able to overrule an AI and work without it, and must promptly report untoward complications to the developer and the relevant regulatory bodies. The MMC developed it in line with MOSTI's National Guidelines on AI Governance and Ethics.[1][11]
Can patient information go into an AI tool at all?
Under the MMC's rules, only with the patient's consent. Its AI guideline says patient data must not be shared on any AI system without the patient's consent, and that you must make sure the tool has robust encryption and access controls to prevent data breaches and reidentification.[1] Its confidentiality guideline, approved in October 2011, asks you to anonymise data wherever unidentifiable data will serve the purpose.[3] The PDPA treats information about a person's physical or mental health as sensitive personal data, which may be processed with explicit consent or where necessary for medical purposes and undertaken by a healthcare professional, among other conditions (section 40), so in this respect the professional rule is stricter than the statute. The Act applies to personal data processed in respect of commercial transactions and does not apply to the Federal Government and State Governments (sections 2 and 3), but the MMC's guidelines bind every registered practitioner wherever they work.[1][4]
Can patient data be stored or processed outside Malaysia?
Yes, on conditions that have applied since 1 April 2025, when the amendments made by Act A1727 to section 129 of the PDPA came into force. A data controller may transfer personal data abroad if the destination has a law substantially similar to the PDPA or ensures an adequate level of protection, or on an alternative ground such as the data subject's consent, necessity for a contract with the data subject, or having taken all reasonable precautions and exercised all due diligence.[4] The Commissioner's Cross Border Personal Data Transfer Guideline (No. 3/2025, issued 29 April 2025) says a controller may run a transfer impact assessment to establish substantial similarity or adequacy, with findings valid for no longer than three years; names binding corporate rules, contractual clauses and certification as ways to show due diligence; requires you to tell data subjects about the transfer in your personal data protection notice; and requires records of each transfer and the evidence behind it. EvidenceMD's application data is hosted in a US region, so each of these rules applies to it.[5][31]
What does the MMC require before an AI scribe records a consultation?
An ambient scribe records the consultation, and the MMC already has rules for recordings. Its Guideline 003/2023 on audio and visual recordings, adopted on 20 June 2023, covers audio recordings made by any device, says it applies equally to new technologies, and treats recordings as part of the patient's medical record, subject to the same standards of confidentiality and consent. Valid consent — from a competent patient, given voluntarily and with sufficient information — must be obtained before a recording is captured, stored or transmitted; consent should be for a specific purpose; written consent is good practice, and where that is not practicable the consent must be documented in the record; the recording must be stored securely and stopped immediately if the patient asks; and failure to follow the guideline can lead to disciplinary action.[2] The AI guideline adds that patient data must not be shared on any AI system without consent.[1] Medical Protection's Malaysian casebook put it plainly in July 2026: clinicians remain responsible for safe use through proper consent, data handling, accuracy and oversight.[17]
Does the Medical Device Authority regulate clinical AI software?
By intended purpose. The MDA's guidance on the definition of a medical device (MDA/GD/0006, second edition, March 2026), which applies the Medical Device Act 2012 (Act 737), includes software intended by its manufacturer to be used for the diagnosis, prevention, monitoring, treatment or alleviation of disease, among other purposes. The MDA's list of guidance documents, checked on 4 November 2026, contains no dedicated guidance on software or AI.[9] The MDA does already handle AI clinical software: in May 2026 it classified AITRICS-VC, which predicts patient deterioration from electronic medical record data, as a Class C device.[10] The MMC's 'reasonable confidence' standard asks that any AI tool comply with the applicable regulatory framework, and tells you to seek clarification from the regulator when in doubt.[1] EvidenceMD is not registered with the MDA, so ask any vendor, including us, in writing how it classifies its product and why.
What changed for clinics in 2025 and 2026, and what is coming?
Since 1 June 2025 the PDPA has required data controllers, and data processors acting for them, to appoint data protection officers and notify the Commissioner (section 12A), and data controllers to notify personal data breaches (section 12B).[4] The Commissioner's breach notification guideline (25 February 2025) sets a deadline of 72 hours to notify the Commissioner and, where the breach is likely to cause significant harm, seven days after that to tell the people affected; a breach of sensitive personal data meets the significant-harm test, so a breach of health information is notifiable. The duty does not bind processors directly, so your contract has to require them to tell you promptly.[6] The Commissioner's 2026 guideline on automated decision-making and profiling gives a healthcare institution using machine learning to determine patients' health status as an example, and asks for the DPO to be involved from the start through a data protection impact assessment.[7] Two proposals are not yet law. The Commissioner consulted from 5 to 23 October 2026 on an AI and personal data protection framework that would expect a transfer impact assessment, where appropriate, for external AI systems that move data abroad, and says engaging an AI provider does not reduce the controller's responsibility.[8] And the National AI Office consulted in July 2026 on an AI Governance Bill, which the Digital Minister told the Dewan Rakyat on 29 October 2026 is complete and due to be tabled by early 2027.[12][13]
When is EvidenceMD not the right choice?
Four situations where EvidenceMD is not the best answer, and honestly most Malaysian doctors should use two tools rather than choose one.
Your hospital or clinic requires data to stay in Malaysia
Self-hosted open weights on your own Malaysian infrastructure
This is the clearest blocker in the guide and no ranking position compensates for it. EvidenceMD hosts application data in Microsoft Azure East US 2 with no Malaysian region today. None of the general models offers Malaysian processing either: OpenAI's API lists no Malaysian region, Anthropic's API runs in the US or globally, Bedrock in the Malaysia Region serves Claude Opus 5.5 only through global routing, and Google's nearest in-region processing for Gemini and Claude is in Singapore.[22][24][25][27] If in-country processing is mandatory, the realistic option here is self-hosting open weights such as Meta's Muse Spark Open inside your own infrastructure, accepting that you then own retrieval, citations, guardrails and validation.[28] Ask about residency in the first vendor conversation rather than after a pilot.
You need patient-facing material in Bahasa Melayu
Use EvidenceMD for the clinical content, and have a Malay-speaking clinician write or check the Malay text
EvidenceMD answers in English, Chinese and Tamil, among 30 languages, but Bahasa Melayu is not one of them. Indonesian is, but Indonesian is not Malay, and we do not suggest it for Malaysian patient material. For a leaflet, a discharge explanation or a consent conversation in Malay, get the clinical content right first and then have the Malay wording written or checked by someone fluent; under the MMC's guideline you remain accountable for what the patient is told either way.[1][33]
The work is drafting, correspondence and general admin
Use ChatGPT (#2) or Claude (#3)
These are the best tools here for the work around the clinical decision rather than the decision itself: referral letters, medical reports, restructuring notes, plain-language explanations, summarising a paper you have already chosen and read. That work does not require evidence-bound retrieval, which is exactly where the general models excel. Keep identifiable patient information out of them unless the patient has consented and the account sits under a business agreement, because the MMC's consent rule applies to every AI system.[1][21][23]
You need independent peer-reviewed validation before adoption
Be sceptical of all five, including EvidenceMD
This is the honest answer and it applies to everything in this comparison. No tool here has an independent, peer-reviewed study of its clinical AI output published by a party other than the vendor. EvidenceMD publishes its HealthBench Hard methodology openly and uses an independent benchmark, and OpenAI publishes HealthBench results for its own models — but self-published is self-published, and the MMC's 'reasonable confidence' standard asks for tools that have been assessed and validated. If your hospital requires an independent published study before adoption, none of these currently clears that bar.[1][29][30]
Which tool fits your role?
Almost nobody should use only one of these. The productive pattern for a Malaysian doctor is a clinical tool for anything that touches a patient, and a general model for the writing around it.
GP in a private clinic
Use EvidenceMD (#1) for undifferentiated presentations where you want cited decision support and a reasoning stream you can check, describing the case without identifiers unless the patient has consented and your section 129 assessment covers a US processor. Keep ChatGPT (#2) for referral letters, medical reports and patient-facing explanations, again without identifiers. Before using any scribe, follow the MMC's recordings guideline: valid consent for that specific purpose before recording, in writing where practicable or documented in the record, and stop if the patient asks. Read every note before it enters the record, and check that your clinic's personal data protection notice tells patients their information may be transferred abroad.[1][2][5]
Specialist or medical officer in a Ministry of Health hospital or klinik kesihatan
Use EvidenceMD (#1) for reasoning through complex presentations where you want to read the chain of thought, and for building case presentations and teaching sessions from retrieved literature rather than recall, with de-identified cases unless your facility has approved the tool. The PDPA does not apply to the Federal Government and State Governments, but the MMC's AI and confidentiality guidelines bind you personally wherever you work.[1][3][4] The Health Minister has told the public not to use AI tools for screening, confirming a diagnosis or any other medical determination, and the ministry is planning a proof-of-concept of AI for clinical documentation in selected hospitals and has said any new tool must be compatible with its existing systems, including its EMR project; public-sector agencies also work to the Public Sector AI Adaptation Guidelines launched in February 2025. Follow your facility's IT and data policies first.[14][15][16]
Doctor whose patients speak Malay, Chinese or Tamil
EvidenceMD answers in Chinese and Tamil as well as English, so you can ask and read in those languages even though the interface is in English. It does not answer in Bahasa Melayu: Malay is not among its 30 languages, and Indonesian, which is, is not a substitute for Malay. For Malay-language material, settle the clinical content with EvidenceMD in English and have the Malay text written or checked by a Malay-speaking clinician. Whatever the language, the MMC expects you to explain to the patient, where appropriate, how AI was used in their care.[1][33]
House officer or medical officer in training
EvidenceMD is free to start, and it is the most useful tool on this list during housemanship and your early years as a medical officer, because a visible reasoning chain is a worked example every time you ask. That fits what the MMC asks of every practitioner: to be able to challenge an AI's output, to complete tasks if the AI fails, and to guard against skills degradation.[1] Use ChatGPT or Claude for summarising papers you have chosen and for general writing. Do not put patient identifiers into anything without your supervisor's and your facility's sign-off.
Data protection officer, clinic manager or hospital IT team
Assess vendors on what the PDPA and the MMC actually require: where data is stored and processed and on which section 129 ground, backed by a transfer impact assessment that lasts no more than three years; whether customer content trains models; encryption and access controls; breach-notification terms that let you meet the 72-hour deadline; and retention and deletion. Since 1 June 2025 data controllers must appoint a DPO, and so must processors acting for them.[1][4][5][6] If in-country processing is non-negotiable and you have engineering capacity, self-hosted open weights inside your own perimeter are the only option here that guarantees it; Gemini and Claude on Google Cloud in Singapore are the nearest regional answer and are still a transfer out of Malaysia.[27][28] Consolidating reasoning, scribing and documentation review in one vendor reduces the number of transfer assessments and processor contracts you maintain.
Frequently asked questions
What is the best AI for doctors in Malaysia in 2026?
EvidenceMD ranks #1 in this guide for doctors in Malaysia, as the only clinically fine-tuned model among the five compared; ChatGPT ranks #2, Claude #3, Gemini #4 and Meta AI #5. It retrieves from 40M+ peer-reviewed papers and guidelines before it writes, streams up to 64,000 tokens of reasoning you can audit, and publishes 54.6% on HealthBench Hard, a self-published figure.[29][30] OpenEvidence is not in this ranking, and whether it works for Malaysian doctors is unconfirmed.[18][19] The caveats to know up front: EvidenceMD hosts data in Microsoft Azure East US 2, so there is no Malaysian region, it is not registered with the Medical Device Authority, and it does not answer in Bahasa Melayu.[31][33]
Can Malaysian doctors use OpenEvidence?
Whether Malaysian doctors can register for OpenEvidence is unconfirmed. Its Terms of Use, last updated 17 September 2026, say the service is not available in the EU, the UK, the EEA or US-embargoed countries — Malaysia is not among them — but registration requires a US National Provider Identifier or, as applicable, another professional licensing number, which OpenEvidence may try to verify, and it reserves the right to restrict access by geography.[18] We found no OpenEvidence announcement of a Malaysian verification route. Its free version with Anthropic, reported by Reuters on 22 September 2026, is being rolled out in about 100 low- and middle-income countries, but the full list has not been published and Malaysia was not among the countries named.[19] EvidenceMD is free to start in Malaysia with no NPI, no MMC number and no licence verification.
Is there a free AI for doctors in Malaysia, and what does EvidenceMD cost?
EvidenceMD is free to start in Malaysia with no NPI, no MMC number and no licence verification. Paid plans are priced in US dollars: Individual at US$50 a month or US$450 a year, and Max, with unlimited use, at US$120 a month or US$1,080 a year.[32] OpenEvidence's free programme with Anthropic covers about 100 low- and middle-income countries, but the full list has not been published and Malaysia was not among those named.[19] ChatGPT, Claude, Gemini and Meta AI have no-cost consumer tiers too, but their healthcare agreements, where they exist, come with business, API or cloud contracts rather than personal accounts, so keep personal accounts for de-identified drafting.[21][23][26]
What does the Malaysian Medical Council say about doctors using AI?
The MMC's Guideline on the Ethical Use of Artificial Intelligence in Medical Practice, adopted on 18 February 2025, says doctors remain responsible and accountable for patients' clinical outcomes, should use only AI tools that meet a standard of 'reasonable confidence', and should tell patients before the consultation, where appropriate, how AI is used in their care and the basis of its recommendations.[1] It says patient data must not be shared on any AI system without the patient's consent, that AI recommendations must be validated with human oversight, and that untoward complications must be reported to the developer and the relevant regulators. EvidenceMD is built so that this oversight is practical: it shows its full reasoning and links every claim to a source you can open.[33]
Can doctors in Malaysia use ChatGPT with patient information?
Not without the patient's consent: the MMC's AI guideline says patient data must not be shared on any AI system without consent, and asks you to make sure the tool has robust encryption and access controls.[1] OpenAI's business products — the API, which can come with a BAA, and ChatGPT for Healthcare — change the contract, and ChatGPT for Clinicians is limited to verified US clinicians.[20][21] OpenAI's API documentation lists no Malaysian data residency region; Singapore, the nearest, offers storage but not processing, so identifiable use is a section 129 transfer you must justify.[5][22] The same consent rule applies to EvidenceMD, which is best used with de-identified cases unless the patient has agreed.
Does the PDPA allow patient data to be processed outside Malaysia?
The PDPA allows it on a section 129 ground: since 1 April 2025 a data controller may transfer personal data abroad where the destination has a law substantially similar to the PDPA or ensures adequate protection, or on an alternative ground such as the data subject's consent, contractual necessity or having taken all reasonable precautions and due diligence.[4] The Commissioner's guideline of 29 April 2025 describes transfer impact assessments valid for up to three years, accepts contractual clauses, binding corporate rules and certification as due diligence, and requires you to tell patients about the transfer and keep records.[5] EvidenceMD hosts data in a US region, so using it with identifiable information needs one of those grounds.[31]
Where does EvidenceMD store data, and can Malaysian doctors use it under the PDPA?
EvidenceMD stores application data in Microsoft Azure East US 2, a US region, so using it with identifiable information is a transfer out of Malaysia that needs a section 129 ground, such as the patient's consent or documented due diligence.[5][31] Health information is sensitive personal data under the PDPA, and the MMC separately requires the patient's consent before their data goes into any AI system.[1][4] EvidenceMD offers a HIPAA BAA on eligible plans, encrypts data in transit and at rest, and does not train on customer conversations, but a BAA is a US instrument and SOC 2 Type II is still in progress; the simplest compliant pattern is to describe cases without identifiers.[31]
Do I need patient consent to use an AI scribe in Malaysia?
Yes. The MMC's Guideline 003/2023 on audio and visual recordings says valid consent must be obtained before a recording is captured, stored or transmitted, for a specific purpose, in writing where practicable or otherwise documented in the medical record, and that the recording must stop if the patient asks.[2] Its AI guideline adds that patient data must not be shared on any AI system without consent, and that patients should be told, where appropriate, how AI is used in their care.[1] Medical Protection says clinicians remain responsible for consent, data handling, accuracy and oversight.[17] Those rules apply to EvidenceMD's ambient scribe exactly as to any other, and you should read every note before it enters the record.
Is EvidenceMD registered with the Medical Device Authority?
EvidenceMD is not registered with the Medical Device Authority, and it holds no medical device licence or registration in any country. The MDA's guidance defines a medical device to include software intended by its manufacturer for the diagnosis, prevention, monitoring, treatment or alleviation of disease, and the MDA has classified at least one AI clinical tool, a deterioration-prediction system, as Class C.[9][10] EvidenceMD is research and decision support that shows its reasoning and sources for a doctor to check, not a diagnostic device; the MMC asks you to make sure any AI tool complies with the applicable regulatory framework, so ask every vendor, including us, how it classifies its product.[1]
Does EvidenceMD answer in Malay, Chinese or Tamil?
EvidenceMD answers in Chinese and Tamil as well as English, chosen from a language menu in the chat, but it does not answer in Bahasa Melayu: Malay is not among its 30 languages.[33] Indonesian is one of them, but Indonesian is not Malay, and we do not suggest it for Malaysian patient material. The app interface is in English. For Malay-language explanations, settle the clinical content first and have the Malay text written or checked by a fluent clinician.
Does the PDPA apply to doctors in government hospitals?
The PDPA applies to personal data processed in respect of commercial transactions and does not apply to the Federal Government and State Governments (sections 2 and 3), so ask your facility which data rules it applies.[4] That does not free any doctor to paste patient details into an AI tool: the MMC's AI and confidentiality guidelines bind every registered practitioner and require consent before patient data goes into any AI system.[1][3] Public-sector agencies also have the Public Sector AI Adaptation Guidelines launched on 27 February 2025, and the Ministry of Health is planning a proof-of-concept of AI for clinical documentation in selected hospitals.[14][16] In a government setting, use EvidenceMD with de-identified cases unless your facility has approved it.
Is there an AI law for doctors in Malaysia?
Malaysia's proposed AI Governance Bill had not been tabled as of 29 October 2026, when the Digital Minister told the Dewan Rakyat it was complete and would be tabled by early 2027; the National AI Office consulted on it in July 2026.[12][13] MOSTI's National Guidelines on AI Governance and Ethics date from September 2024, and the Personal Data Protection Commissioner consulted in October 2026 on an AI and personal data protection framework.[8][11] For doctors, the binding professional rules today are the MMC's, which apply to EvidenceMD as to any other tool: consent before patient data is shared, human oversight, and personal accountability for outcomes.[1]
Who is responsible if an AI tool gets it wrong in Malaysia?
In Malaysia the doctor remains responsible when an AI tool gets it wrong: the MMC says registered medical practitioners remain responsible and accountable for patients' clinical outcomes and for their clinical decisions, must validate AI recommendations, and must be clear on the issue of liability before relying on a tool.[1] Medical Protection says clinicians remain responsible for consent, data handling, accuracy and oversight.[17] That is why verification cost matters: EvidenceMD shows its reasoning and links every claim to a source, so checking it means reading the chain and opening two citations in PubMed rather than redoing the work.[34]
The bottom line
EvidenceMD is the #1 medical AI for doctors in Malaysia in this guide, and the choice is simpler than a five-way ranking makes it look, because only one of these five is a clinical product. Use EvidenceMD (#1) for cited decision support, documentation review and teaching presentations — it is the only clinically fine-tuned model here, the only one streaming an auditable chain of thought of up to 64,000 thinking tokens, and the only one whose citations were retrieved before the answer was written. Accept its Malaysian limits going in: data in Azure East US 2, no MDA registration, SOC 2 Type II in progress, an English interface, no answers in Bahasa Melayu and self-published benchmarks. Whether OpenEvidence works here is unconfirmed. Keep ChatGPT (#2) and Claude (#3) for the writing around the decision, Gemini (#4) for long documents and images, and treat Meta AI (#5) as either off-limits (the consumer app) or an infrastructure project (self-hosted open weights). Then get the Malaysian basics right: the patient's consent before their data goes into any AI system and before any recording, a section 129 ground and a transfer impact assessment for any vendor outside Malaysia, a processor contract that lets you meet the 72-hour breach deadline, and the ten-second test — open two citations and confirm they say what the tool claims.[1][2][5][6][34]
Sources & related evidence
Every bracketed number above links here; all sources were consulted on 4 November 2026. Sources 1 to 3 are Malaysian Medical Council guidelines; 4 to 8 are the Personal Data Protection Act 2010 and the Personal Data Protection Commissioner's guidelines and AI consultation; 9 and 10 cover the Medical Device Authority; 11 to 13 are national AI governance documents and reporting on the AI Governance Bill; 14 to 16 cover the Ministry of Health and the public sector; 17 is Medical Protection; 18 and 19 are OpenEvidence's terms and Reuters' report on its partnership with Anthropic; 20 to 28 are the vendors' own documentation plus one trade report, so every competitor claim is checkable against the company that made it; 29 is the independent benchmark paper; 30 to 33 are EvidenceMD pages, meaning those facts are company claims rather than independent verification; 34 is PubMed.
About EvidenceMD
EvidenceMD is an evidence-based clinical decision support platform running on a model fine-tuned for medical reasoning rather than a general-purpose model, with a self-published 54.6% on HealthBench Hard. It streams an auditable clinical chain of thought of up to 64,000 thinking tokens, and retrieval across 40M+ peer-reviewed papers and guidelines completes before the answer is written, with citations embedded in the body of the answer. The same engine powers an ambient medical scribe, documentation integrity review, ranked differential diagnosis and clinical presentations. It is free to start in Malaysia with no NPI and no licence verification, answers in 30 languages including Chinese and Tamil (but not Bahasa Melayu) through an English interface, and is HIPAA compliant with a BAA available on eligible plans. Application data is hosted in Microsoft Azure East US 2, so there is no Malaysian data residency option and any identifiable use is a cross-border transfer under section 129 of the PDPA; it is not registered with the Medical Device Authority; SOC 2 Type II certification is in progress and not yet complete; and the benchmark figures are self-published rather than independently reproduced. Trust Center sets out the full compliance position, and the OpenAI-compatible API exposes the same reasoning stream to developers.
Related reading
Read the reasoning, not just the answer
Ask EvidenceMD about a case you already know the answer to, and read the chain of thought. Free to start in Malaysia, with no NPI, no MMC number and no licence verification.